



Vol. 13. Núm. 34.
Páginas 1985-1994 (Mayo 2021)

Actualización
Vasculitis de gran vaso: arteritis de células gigantes y arteritis de Takayasu

Large-vessel vasculitis: giant cell arteritis and Takayasu's arteritis

J. Álvarez-TroncosoaB. Gracia-TellobM. FreirecB. Sopeñac
Doi : https://10.1016/j.med.2021.05.011
Opciones
Resumen

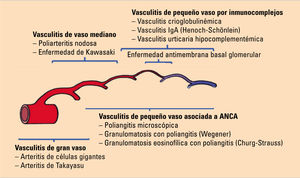
Las vasculitis de gran vaso afectan predominantemente a la arteria aorta y sus ramas y se clasifican en dos entidades principales: la arteritis de células gigantes (ACG) y la arteritis de Takayasu (ATK). La ACG suele presentarse con cefalea temporal de reciente comienzo, claudicación mandibular e hipersensibilidad del cuero cabelludo. Algunos pacientes presentarán también síntomas visuales (amaurosis fugaz y neuritis óptica anterior) y manifestaciones sistémicas como la polimialgia reumática, la fiebre y la pérdida de peso. La biopsia de arteria temporal es una ayuda importante en su diagnóstico. Otras herramientas son la ecografía de arterias temporales, la tomografía por emisión de positrones combinada con tomografía computarizada (PET-TC) y la angiorresonancia magnética (RM). Los glucocorticoides (GC) son el pilar del tratamiento de la ACG, reservando la asociación de tocilizumab o metotrexato para pacientes con recurrencias o con toxicidad importante relacionada con los corticoides. La aparición de síntomas en la ATK tiende a ser subaguda, lo que a menudo conduce a un retraso diagnóstico. El diagnóstico clínico de la ATK puede ser realizado en base a hallazgos clínicos sugestivos (síntomas constitucionales, carotidinia, hipertensión, pulsos disminuidos o ausentes y/o soplos arteriales en pacientes de menos de 40 años) y una prueba de imagen que muestre el estrechamiento vascular de la aorta y/o sus ramas primarias. La angio-TC ayuda a detectar complicaciones de la vasculitis y la PET/TC al evaluar la respuesta al tratamiento. El pilar del tratamiento de la ATK son los GC sistémicos, recomendando la asociación precoz de un fármaco ahorrador de esteroides debido a la alta tasa de recaída.

Palabras clave
Vasculitis de grandes vasos
Arteritis de células gigantes
Arteritis de Takayasu
Abstract

Large-vessel vasculitis predominantly affects the aorta and its branches and is classified into two main entities: giant cell arteritis (GCA) and Takayasu arteritis (TKA). GCA usually presents with new-onset temporal headache, jaw claudication and scalp hypersensitivity. Some patients also have visual symptoms (amaurosis fugax and anterior optic neuritis) and systemic manifestations such as polymyalgia rheumatica, fever and weight loss. Temporal artery biopsy is an important diagnostic aid. Other tools include temporal artery ultrasound, positron emission tomography combined with computed tomography (PET-CT) and magnetic resonance angiography (MRA). Glucocorticoids (GC) are the mainstay of treatment for GCA, reserving combining with tocilizumab or methotrexate for patients with recurrences or significant corticosteroid-related toxicity. The onset of symptoms in TKA tends to be subacute, often resulting in diagnostic delay. A clinical diagnosis of TKA can be based on suggestive clinical findings (constitutional symptoms, carotid artery disease, hypertension, decreased or absent pulses and/or arterial murmurs in patients under 40 years of age) and an imaging test showing vascular narrowing of the aorta and/or its primary branches. Angio-CT helps to detect complications of vasculitis and PET/CT to assess response to treatment. Systemic GCs are the mainstay of treatment for TKA, and the early combination of a steroid-sparing drug due to the high rate of relapse.

Keywords
Large vessel vasculitis
Giant cell arteritis
Takayasu's arteritis

Identifíquese

¿Aún no es suscriptor de la revista?

Comprar el acceso al artículo

Comprando el artículo el pdf del mismo podrá ser descargado

Teléfono para incidencias

De lunes a viernes de 9h a 18h (GMT+1) excepto los meses de julio y agosto que será de 9 a 15h

Llamadas desde España 932 415 960
Llamadas desde fuera de España +34 932 415 960
Bibliografía
[1]
J.C. Jennette
202106080541598568
202106080541598569
, R.J. Falk, P.A. Bacon, N. Basu, M.C. Cid, F. Ferrario, et al.
2012 revised International Chapel Hill Consensus Conference Nomenclature of Vasculitides.
Arthritis Rheum., (2013), 65 pp. 1-11
[2]
D. Saadoun
2021060805415985610
, M. Vautier, P. Cacoub.
Medium- and Large-vessel vasculitis.
Circulation., (2021), 143 pp. 267-282
[3]
A. Kawasaki
2021060805415985611
, V. Purvin.
Giant cell arteritis: An updated review.
Acta Ophthalmol., (2009), 87 pp. 13-32
[4]
M.A. González-Gay
2021060805415985612
, J.A. Miranda-Filloy.
«Silent» giant cell arteritis.
South Med J., (2006), 99 pp. 1204-1205
[5]
P. Yu-Wai-Man
2021060805415985613
, M.R. Dayan.
Giant cell arteritis with normal inflammatory markers.
Acta Ophthalmol Scand., (2007), 85 pp. 460
[6]
M. Isobe
2021060805415985614
.
Takayasu arteritis revisited: current diagnosis and treatment.
Int J Cardiol., (2013), 168 pp. 3-10
[7]
S. Simon
2021060805415985615
, J. Ninan, P. Hissaria.
Diagnosis and management of giant cell arteritis: Major review.
Clin Exp Ophthalmol., (2021), 49 pp. 169-185
[8]
R. Serra
2021060805415985616
, L. Butrico, F. Fugetto, M.D. Chibireva, A. Malva, G. De Caridi, et al.
Updates in pathophysiology, diagnosis and management of Takayasu arteritis.
Ann Vasc Surg., (2016), 35 pp. 210-225
[9]
C. Labarca, M.J. Koster, C.S. Crowson, A. Makol, S.R. Ytterberg, E.L. Matteson, et al.
Predictors of relapse and treatment outcomes in biopsy-proven giant cell arteritis: a retrospective cohort study.
Rheumatology (Oxford)., (2016), 55 pp. 347-356
[10]
E. Hachulla
2021060805415985617
, V. Boivin, U. Pasturel-Michon, A.L. Fauchais, J. Bouroz-Joly, M. Pérez-Cousin, et al.
Prognostic factors and long-term evolution in a cohort of 133 patients with giant cell arteritis.
Clin Exp Rheumatol., (2001), 19 pp. 171-176
[11]
K. Ishikawa, S. Maetani.
Long-term outcome for 120 Japanese patients with Takayasu's disease. Clinical and statistical analyses of related prognostic factors.
Circulation., (1994), 90 pp. 1855-1860
[12]
F. Buttgereit
2021060805415985618
2021060805415985619
, C. Dejaco, E.L. Matteson, B. Dasgupta.
Polymyalgia rheumatica and giant cell arteritis: a systematic review.
JAMA., (2016), 315 pp. 2442-2458
[13]
A. Chakrabarty, S. Mackie, C. Harden, A.W. Morgan.
Temporal artery biopsy: audit of histological diagnosis.
Rheumatology (Oxford)., (2020), 59 pp. 678-679
[14]
I.C. Aranda-Valera, S. García Carazo, I. Monjo Henry, E. De Miguel Mendieta.
Diagnostic validity of Doppler ultrasound in giant cell arteritis.
Clin Exp Rheumatol., (2017), 35 pp. 123-127
[15]
E. De Miguel, A. Roxo, C. Castillo, D. Peiteado, A. Villalba, E. Martín-Mola.
The utility and sensitivity of colour Doppler ultrasound in monitoring changes in giant cell arteritis.
Clin Exp Rheumatol., (2012), 30 pp. S34-S38
[16]
C. Agard, J.-H. Barrier, B. Dupas, T. Ponge, A. Mahr, G. Fradet, et al.
Aortic involvement in recent-onset giant cell (temporal) arteritis: a case-control prospective study using helical aortic computed tomodensitometric scan.
Arthritis Rheum., (2008), 59 pp. 670-676
[17]
G.G. Hunder
2021060805415985620
2021060805415985621
, D.A. Bloch, B.A. Michel, M.B. Stevens, W.P. Arend, L.H. Calabrese, et al.
The American College of Rheumatology 1990 criteria for the classification of giant cell arteritis.
Arthritis Rheum., (1990), 33 pp. 1122-1128
[18]
C. Dejaco
2021060805415985622
2021060805415985623
, S. Ramiro, C. Duftner, F.L. Besson, T.A. Bley, D. Blockmans, et al.
EULAR recommendations for the use of imaging in large vessel vasculitis in clinical practice.
Ann Rheum Dis., (2018), 77 pp. 636-643
[19]
I. Yamada, T. Nakagawa, Y. Himeno, Y. Kobayashi, F. Numano, H. Shibuya.
Takayasu arteritis: diagnosis with breath-hold contrast-enhanced three-dimensional MR angiography.
[20]
I. Yamada, T. Nakagawa, Y. Himeno, F. Numano, H. Shibuya.
Takayasu arteritis: evaluation of the thoracic aorta with CT angiography.
Radiology., (1998), 209 pp. 103-109
[21]
R.H.J.A. Slart
2021060805415985624
2021060805415985625
.
FDG-PET/CT(A) imaging in large vessel vasculitis and polymyalgia rheumatica: joint procedural recommendation of the EANM, SNMMI, and the PET Interest Group (PIG), and endorsed by the ASNC.
Eur J Nucl Med Mol Imaging., (2018), 45 pp. 1250-1269
[22]
W.P. Arend
2021060805415985626
2021060805415985627
, B.A. Michel, D.A. Bloch, G.G. Hunder, L.H. Calabrese, S.M. Edworthy, et al.
The American College of Rheumatology 1990 criteria for the classification of Takayasu arteritis.
Arthritis Rheum., (1990), 33 pp. 1129-1134
[23]
B.K. Sharma
2021060805415985628
, S. Jain, S. Suri, F. Numano.
Diagnostic criteria for Takayasu arteritis.
Int J Cardiol., (1996), 54 pp. S141-S147
[24]
B. Hellmich
2021060805415985629
2021060805415985630
, A. Agueda, S. Monti, F. Buttgereit, H. de Boysson, E. Brouwer, et al.
2018 Update of the EULAR recommendations for the management of large vessel vasculitis.
Ann Rheum Dis., (2020), 79 pp. 19-30
[25]
P.D. Aiello, J.C. Trautmann, T.J. McPhee, A.R. Kunselman, G.G. Hunder.
Visual prognosis in giant cell arteritis.
Ophthalmology., (1993), 100 pp. 550-555
[26]
G.G. Hunder, S.G. Sheps, G.L. Allen, J.W. Joyce.
Daily and alternate-day corticosteroid regimens in treatment of giant cell arteritis: comparison in a prospective study.
Ann Intern Med., (1975), 82 pp. 613-618
[27]
F. Buttgereit
2021060805415985631
, J.A.P. da Silva, M. Boers, G.-R. Burmester, M. Cutolo, J. Jacobs, et al.
Standardised nomenclature for glucocorticoid dosages and glucocorticoid treatment regimens: current questions and tentative answers in rheumatology.
Ann Rheum Dis., (2002), 61 pp. 718-722
[28]
P.M. Villiger
2021060805415985632
2021060805415985633
, S. Adler, S. Kuchen, F. Wermelinger, D. Dan, V. Fiege, et al.
Tocilizumab for induction and maintenance of remission in giant cell arteritis: a phase 2, randomised, double-blind, placebo-controlled trial.
Lancet (London, England)., (2016), 387 pp. 1921-1927
[29]
J.H. Stone
2021060805415985634
2021060805415985635
, K. Tuckwell, S. Dimonaco, M. Klearman, M. Aringer, D. Blockmans, et al.
Trial of Tocilizumab in Giant-Cell Arteritis.
N Engl J Med., (2017), 377 pp. 317-328
[30]
A.D. Mahr
2021060805415985636
, J.A. Jover, R.F. Spiera, C. Hernández-García, B. Fernández-Gutiérrez, M.P. Lavalley, et al.
Adjunctive methotrexate for treatment of giant cell arteritis: an individual patient data meta-analysis.
Arthritis Rheum., (2007), 56 pp. 2789-2797
[31]
M. De Silva
2021060805415985637
, B.L. Hazleman.
Azathioprine in giant cell arteritis/polymyalgia rheumatica: a double-blind study.
Ann Rheum Dis., (1986), 45 pp. 136-138
[32]
C.A. Langford
2021060805415985638
, D. Cuthbertson, S.R. Ytterberg, N. Khalidi, P.A. Monach, S. Carette, et al.
A randomized, double-blind trial of abatacept (CTLA-4Ig) for the treatment of Takayasu arteritis.
Arthritis Rheumatol (Hoboken, NJ)., (2017), 69 pp. 846-853
[33]
M.S. Lee
2021060805415985639
, S.D. Smith, A. Galor, G.S. Hoffman.
Antiplatelet and anticoagulant therapy in patients with giant cell arteritis.
Arthritis Rheum., (2006), 54 pp. 3306-3309
[34]
C.T. Berger, V. Greiff, S. John, K.F. Koenig, M.B. Bigler, M. Recher, et al.
Risk factors for pneumocystis pneumonia in giant cell arteritis: a single-centre cohort study.
Clin Exp Rheumatol., (2015), 33
[35]
K. Maksimowicz-McKinnon, T.M. Clark, G.S. Hoffman.
Limitations of therapy and a guarded prognosis in an American cohort of Takayasu arteritis patients.
Arthritis Rheum., (2007), 56 pp. 1000-1009
[36]
C.E. Fields, T.C. Bower, L.T. Cooper, T. Hoskin, A.A. Noel, J.M. Panneton, et al.
Takayasu's arteritis: operative results and influence of disease activity.
J Vasc Surg., (2006), 43 pp. 64-71
[37]
J.C. Mason
2021060805415985640
.
Takayasu arteritis: surgical interventions.
Curr Opin Rheumatol., (2015), 27 pp. 45-52